
Erectile Dysfunction Treatment
The quiet change that becomes hard to ignore
Erectile dysfunction often starts in a way that is easy to dismiss. Less firmness. Less consistency. More doubt. More pressure. Then comes the part men usually do not say out loud: the confidence drops, the mind gets louder, and the problem starts to repeat itself. That cycle is real, and it is one of the main reasons ED should be addressed early. In many men, it is not just about sex. It is about blood flow, hormones, sleep, stress and overall health.
When Erections Start Changing, Life Changes Too
At our Calgary clinic, we look at the whole picture. We offer acoustic wave therapy (LiSWT), PRP, testosterone replacement therapy when indicated, and functional medicine and longevity assessment, to find the cause and build a treatment plan that makes sense for the individual.
ED can be an early sign that the body needs attention. It is often linked to vascular problems, high blood pressure, diabetes, insulin resistance, smoking, excess weight and poor circulation. It can appear before more serious heart problems do, which is why we treat it as an important health signal rather than a private nuisance.
BLOOD FLOW |
NITRIC OXIDE |
HEALTHY VESSELS |
BALANCED HORMONES |
NERVE FUNCTION |
SLEEP & STRESS |
METABOLIC HEALTH |
MEDICATIONS |
This is why a symptom-only approach often does not solve the problem for long. When the root cause is not addressed, the underlying process continues, and medication eventually stops working.
Why Choose Live Younger for ED Treatment
We do not treat ED as one isolated symptom. We assess hormones, metabolic health, cardiovascular risk, sleep, stress and medications to find what is actually driving it, then treat that.
This is not radial pressure-wave treatment. We use a focused acoustic approach with adjustable depth, so treatment can be tailored to the area being treated.
Care is delivered in a professional medical setting by an experienced team, with the privacy and straightforward conversation this deserves.
A Simple Way to Understand Where You Are

Many men struggle to put words to what is happening. This simple, validated scale offers a shared language for where you are right now.
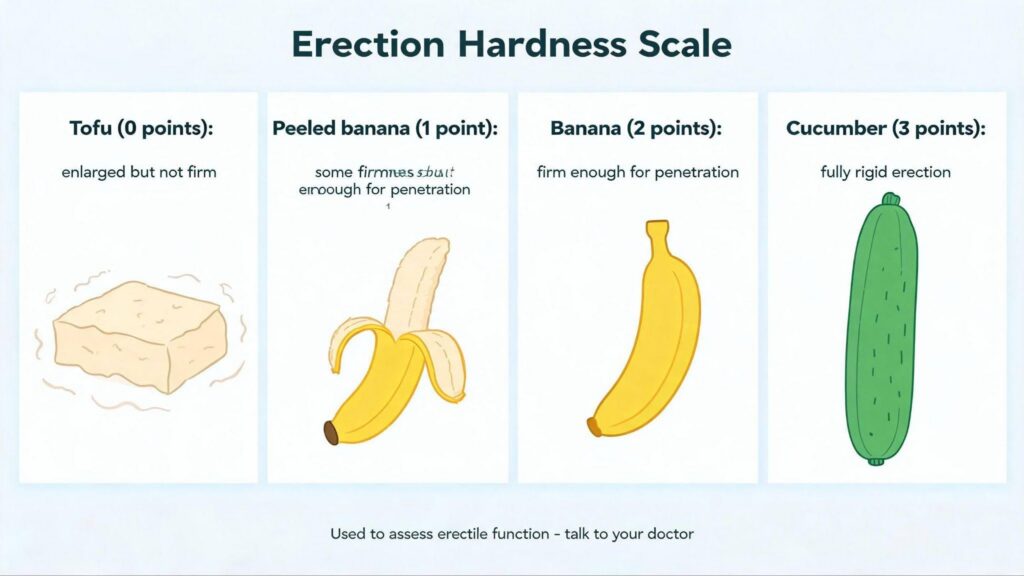
Many men recognise themselves in the middle of this scale. That is often exactly where treatment can still make a real difference.
Common Causes of ED
One of the most common causes. Blood vessels need to relax and open well for an erection to happen. When they are stiff or narrowed, erections are weaker.
Nitric oxide helps blood vessels relax. If that signalling is low, blood flow into the penis drops and erection quality suffers.
Stress and anxiety make erections worse, and so do poor sleep, depression and relationship strain. One difficult experience lowers confidence, and lower confidence makes the next experience harder. That loop needs a real plan.
Testosterone matters, but it is not the only hormone that matters. We look at the whole pattern: testosterone, estradiol, SHBG, thyroid function, cortisol, prolactin and insulin. Some men need testosterone replacement therapy. Others do not.
Medications that can contribute:
- Antidepressants
- Some blood pressure medications
- Opioids
- Sedatives
- Some antipsychotics
- Finasteride and related hair-loss medications
Recreational drugs and alcohol:
- Opioids
- Cannabis
- Cocaine
- Methamphetamine
- MDMA
- Heavy alcohol use
Endocrine-disrupting chemicals:
- Phthalates (found in plastics)
- BPA
- Certain pesticides
- Triclosan
Our Treatments
Acoustic wave therapy (LiSWT)
Acoustic wave therapy (LiSWT) is our main ED treatment. It is non-invasive, quick, and generally very well tolerated. Most studies report low rates of side effects, and serious long-term problems have not been a major finding in the clinical literature.
Some men notice change early. In our clinic, many patients experience improvements soon after beginning the protocol. We look after nitric oxide, hormones, and other contributing factors alongside the therapy, which may help explain why results can begin early.
This is not a radial pressure-wave treatment. We use a focused acoustic approach with adjustable depth, so treatment can be tailored to the area being treated.
PRP Therapy
PRP uses your own platelet-rich plasma to deliver growth factors that may support tissue repair and sexual function. It can be used on its own in selected cases, but it is often most useful as part of a broader treatment plan.
Testosterone replacement therapy
If testing shows true low testosterone, TRT may help improve libido, energy, mood, body composition, and erectile function in selected men. It is not the answer for everyone, but when it is indicated, it can be an important part of treatment.
Our Other Treatments
1. PRP Therapy
PRP uses your own platelet-rich plasma to deliver growth factors that may support tissue repair and sexual function. It can be used on its own in selected cases, but it is often most useful as part of a broader treatment plan.
2. Testosterone Replacement Therapy
If testing shows true low testosterone, TRT may help improve libido, energy, mood, body composition and erectile function in selected men. It is not the answer for everyone, but when it is indicated it can be an important part of treatment.
3. Functional Medicine and Longevity Care
For many men, ED is part of a larger pattern. We look at insulin resistance, inflammation, sleep problems, cortisol imbalance, cardiovascular risk, weight gain, mood, brain chemistry and hormone balance. ED is often not just about the penis. It can reflect what is happening throughout the body.
4. Psychogenic ED Support
If anxiety, stress, confidence loss or relationship strain are part of the picture, we also offer support for psychogenic ED, including hypnotherapy and life coaching where appropriate. The goal is to break the cycle, restore confidence and reduce the pressure that keeps the problem going.
5. Evidence highlight box, full width, teal:
Multiple randomised controlled trials and meta-analyses demonstrate that low-intensity shockwave therapy significantly improves erectile function compared with placebo, with clinically meaningful improvements in both erectile rigidity and blood flow. The strongest results are seen in men with vasculogenic erectile dysfunction, where studies show substantial increases in functional erections (EHS of 3 or more) and validated erectile function scores (IIEF).
Stress and confidence
Stress and anxiety can make erections worse. So can poor sleep, depression, and relationship strain. Many men get stuck in a loop: one difficult experience lowers confidence, and lower confidence makes the next experience harder. That is a real pattern, and it needs a real plan.
When to Book an Assessment
Consider booking an assessment if you notice:
- Less firmness
- Less consistent erections
- Reduced libido
- Confidence dropping
- More worry around sex
- ED alongside high blood pressure, diabetes, obesity, sleep apnea, or low energy
Ready to Find the Cause, Not Just Mask It?
Frequently Asked Questions
Yes. It is generally very well tolerated and non-invasive, with low rates of side effects in studies.
No. It tends to work best for men with blood-flow-related ED, and results depend on the cause and severity.
Some men notice changes after the first treatment. Others improve more gradually over the treatment series.
Many men do four to six treatments. More severe cases may need up to twelve. Some men benefit from PRP as well.
No. It is a focused acoustic treatment with adjustable depth, not a superficial radial pressure-wave device.
Yes, if testosterone is truly low and the symptoms fit. TRT can improve sexual function in selected men.
Yes. ED can be an early sign of vascular or cardiovascular problems.
Where You Can Find Us
References
- The Princeton IV Consensus Recommendations for the Management of Erectile Dysfunction and Cardiovascular Disease. Mayo Clinic Proceedings. 2024.
- Erectile Dysfunction as an ASCVD Risk-Enhancing Factor. American College of Cardiology. 2024.
- Low-intensity shockwave therapy for erectile dysfunction. Cochrane Database of Systematic Reviews. 2025.
- The recommended treatment protocol for low-intensity shockwave therapy for erectile dysfunction: a narrative review. 2024.
- Truths and myths of low-intensity shock wave therapy for erectile dysfunction. Yale School of Medicine.
- Testosterone replacement in men with sexual dysfunction. 2024.
- A logical approach to treating erectile dysfunction. Harvard Health.
- Erectile Dysfunction and Heart Disease. Brown Health.
- What can erectile dysfunction tell you about heart health? UChicago Medicine.
- Cardiovascular Implications of Erectile Dysfunction. Circulation. 2011.
- Erectile Dysfunction. Mayo Clinic.
- Fatima K, et al. Efficacy of low-intensity extracorporeal shockwave therapy for erectile dysfunction: updated meta-analysis of randomized trials. Future Science OA. 2025. PubMed
- Meta-analysis of 16 RCTs (1,064 patients). PubMed
- Jackson G, Montorsi P, Adams MA. Erectile dysfunction and coronary artery disease prediction: evidence-based guidance and consensus. Int J Clin Pract. 2010;64(7):848–857. PubMed
- Vlachopoulos C, et al. Unfavourable endothelial and inflammatory state in erectile dysfunction patients with or without coronary artery disease. Eur Heart J. 2006;27(22):2640–2648. PubMed
- Miner M, Nehra A, Jackson G, et al. All men with vasculogenic erectile dysfunction require a cardiovascular workup. Am J Med. 2014;127(3):174–182. PubMed
- Clavijo RI, Kohn TP, Kohn JR, Ramasamy R. Effects of low-intensity extracorporeal shockwave therapy on erectile dysfunction: a systematic review and meta-analysis. J Sex Med. 2017;14(1):27–35. PubMed
- Lu Z, Lin G, Reed-Maldonado A, et al. Low-intensity extracorporeal shock wave treatment improves erectile function: a systematic review and meta-analysis. Eur Urol. 2017;71(2):223–233. PubMed
- Gruenwald I, Appel B, Vardi Y. Low-intensity shock wave therapy — a novel effective treatment for erectile dysfunction in severe ED patients who respond poorly to PDE5 inhibitors. J Sex Med. 2012;9(1):259–264. PubMed
- Epifanova MV, et al. Platelet-rich plasma therapy for male sexual dysfunction: myth or reality? Sex Med Rev. 2020;8(1):106–113. PubMed
- Matz EL, Pearlman AM, Terlecki RP. Safety and feasibility of platelet rich fibrin matrix injections for treatment of common urologic conditions. Investig Clin Urol. 2018;59(1):61–65. PubMed
- Corona G, et al. Testosterone and metabolic syndrome: a meta-analysis study. J Sex Med. 2011;8(1):272–283. PubMed
- Traish AM, Miner MM, Morgentaler A, Zitzmann M. Testosterone deficiency. Am J Med. 2011;124(7):578–587. PubMed
- Brownlee M. Biochemistry and molecular cell biology of diabetic complications. Nature. 2001;414(6865):813–820. PubMed
- DeFronzo RA, Ferrannini E. Insulin resistance: a multifaceted syndrome. Diabetes Care. 1991;14(3):173–194. PubMed
- Meeker JD, Ferguson KK. Relationship between urinary phthalate and bisphenol A concentrations and serum thyroid measures in U.S. adults. Environ Health Perspect. 2011;119(10):1396–1402. PubMed
- Lv Y, et al. Association between triclosan exposure and male reproductive hormones. Environ Res. 2016;147:312–318. PubMed
- McCabe MP, Sharlip ID, Atalla E, et al. Definitions of sexual dysfunctions in women and men: a consensus statement. J Sex Med. 2016;13(2):135–143. PubMed
- Kalmbach DA, Pillai V, Kingsberg SA, Ciesla JA. The impact of insomnia on sexual function. Sleep Med Rev. 2015;22:23–31. PubMed
- McCabe MP, Althof SE. A systematic review of the psychosocial outcomes associated with erectile dysfunction. J Sex Med. 2014;11(2):347–363. PubMed